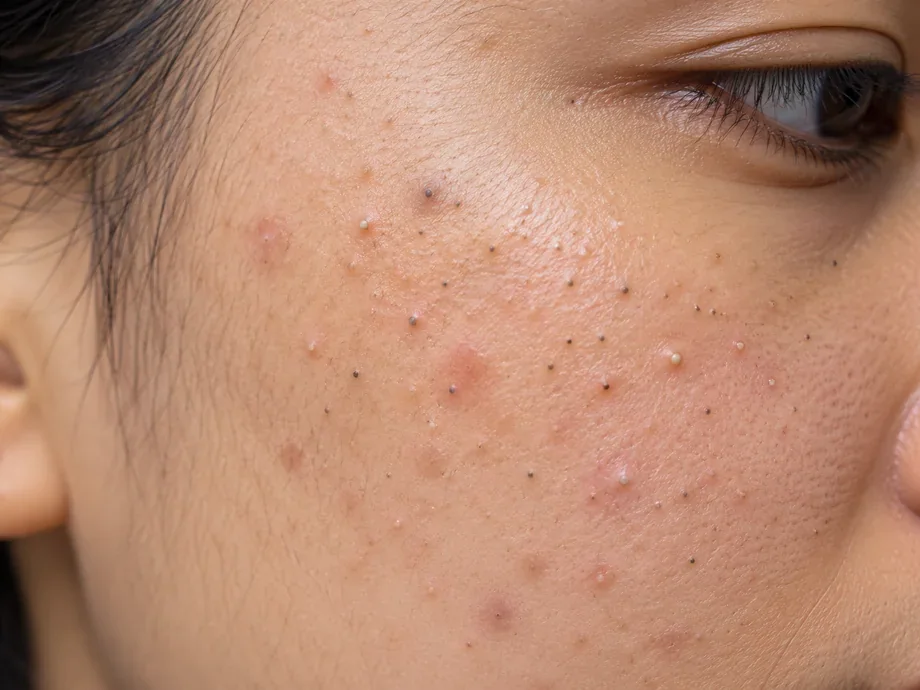
Whiteheads & blackheads
Small clogged pores and tiny bumps, often with little redness. This is common in early or mild acne.
From blackheads and inflamed pimples to deep, painful acne on the face, chest or back, effective care starts with identifying your acne type and scarring risk — not trying product after product.
Consultation fee ₹800 · Pre-booking required · No advance booking payment
MBBS (IMS-BHU), MD (IMS-BHU)
Dermatologist & Venereologist · Dehradun
Dr Neeraj Garg completed both MBBS and MD at the Institute of Medical Sciences, Banaras Hindu University (IMS-BHU). He provides evidence-based assessment for skin, hair, nail and sexually transmitted conditions, with individualised care, clear counselling and patient privacy.
 MBBS + MDBoth from IMS-BHU
Some breakouts are mostly blocked pores; others are inflamed or deep. Different acne patterns often need different treatment plans.
Small clogged pores and tiny bumps, often with little redness. This is common in early or mild acne.
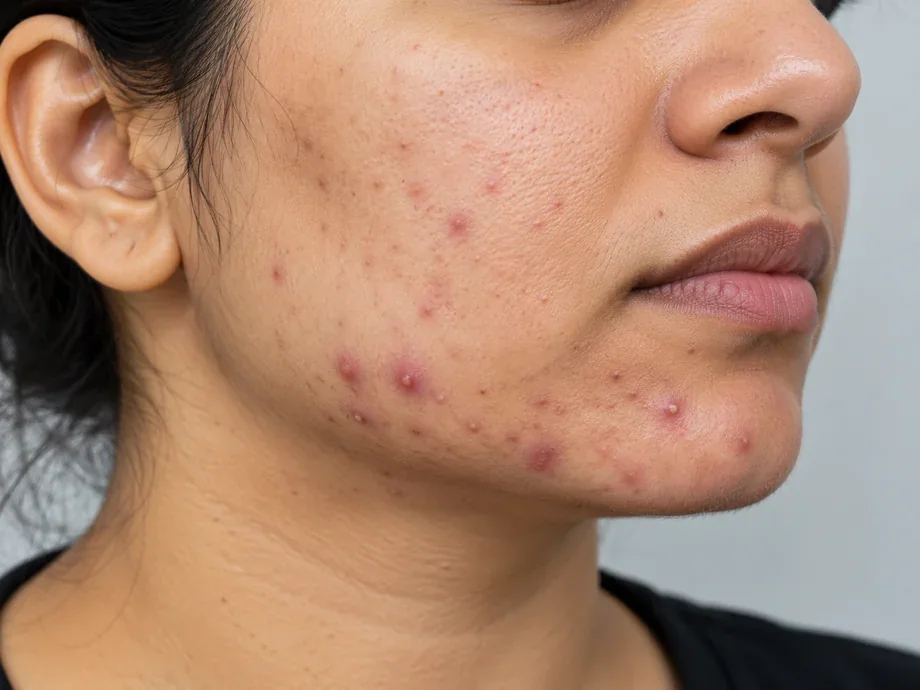
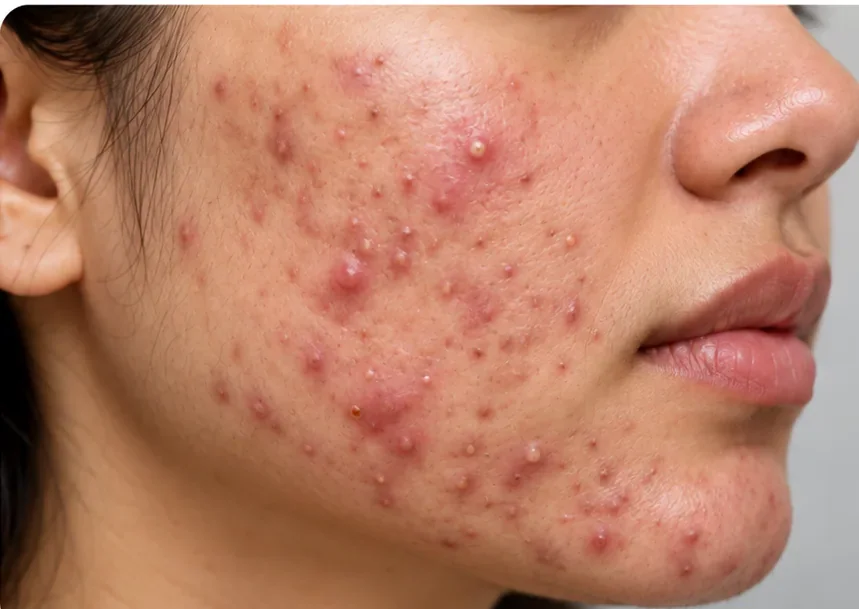
Inflamed or pus-filled breakouts that can sting, recur and may leave dark marks after healing.
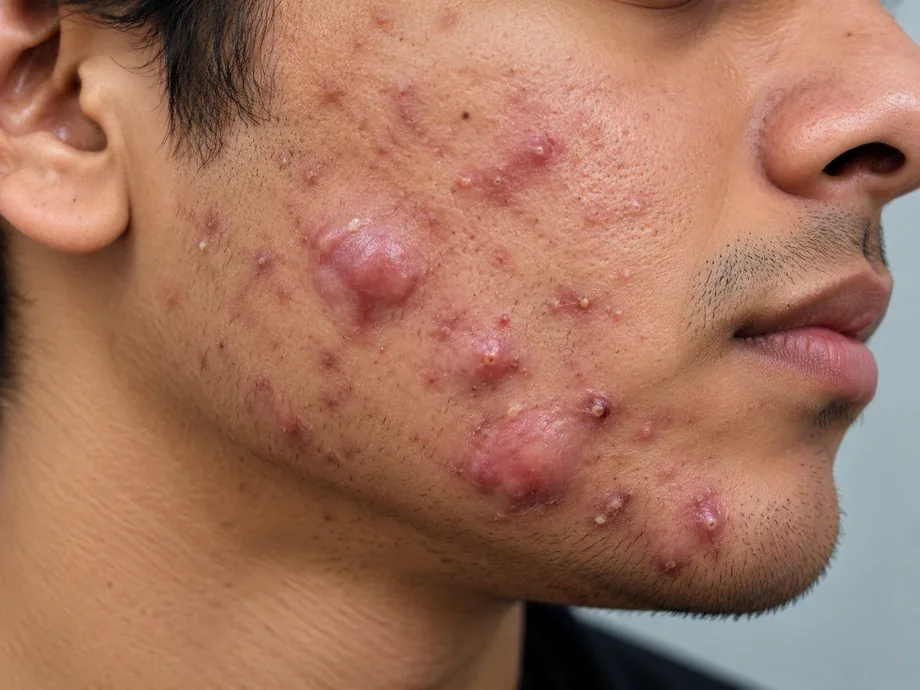
Deeper tender lumps with a higher risk of acne scars. Early treatment is important in this type.
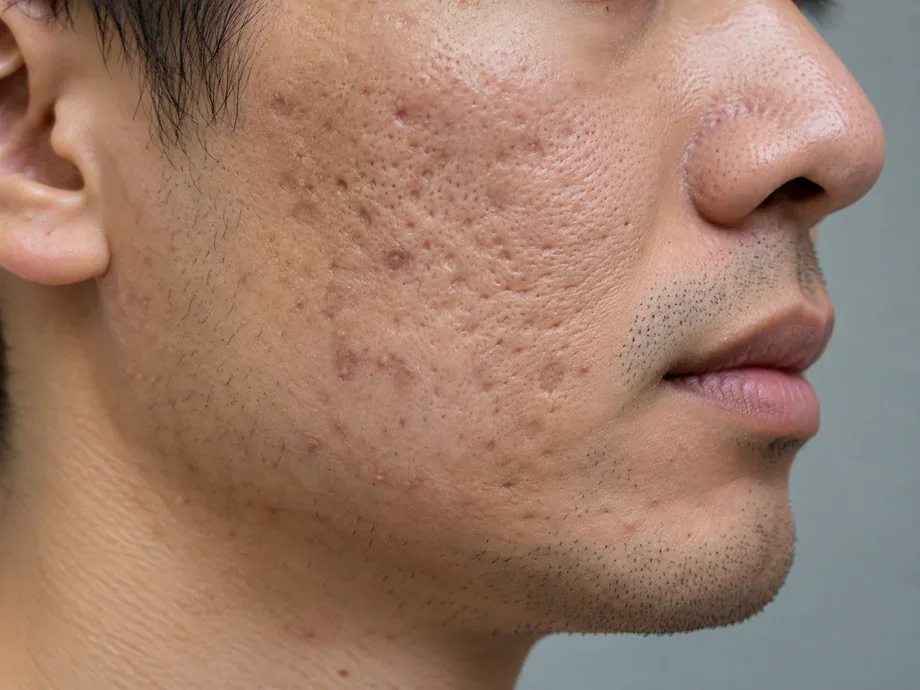
Brown/red marks often fade over time with suitable care. Pitted or raised scars involve a change in skin texture and may need separate treatment after active breakouts are controlled. Explore acne scar care →
Some conditions need a different diagnosis and treatment plan. A closer examination can prevent inappropriate acne creams or repeated self-treatment.
Inflammation or infection of hair follicles, sometimes involving the back and chest, can resemble acne.
Facial flushing, redness and papules or pustules may occur without the blackheads typical of acne.
Small inflammatory bumps may be triggered or worsened by topical steroids and require a different approach.
Not all acne needs intensive treatment. These signs suggest that a personalised clinical assessment may help prevent prolonged breakouts or permanent marks.
Large tender nodules, cyst-like lesions or repeated swelling deserve early review because the risk of scarring is higher.
If spots leave persistent colour changes or pits in the skin, address active acne rather than waiting for damage to accumulate.
Seek advice when consistent over-the-counter care is not helping, acne keeps recurring or breakouts affect day-to-day confidence.
You do not need to wait for severe acne. Assessment can help determine whether basic skincare, prescription medicines or closer follow-up is appropriate.
Book an acne consultation ↗Treatment is selected according to severity, skin sensitivity, previous medicines, scarring risk and relevant medical history. These are examples of pathways — not a prescription.
Gentle cleansing and targeted medicines such as retinoids, benzoyl peroxide or azelaic acid may be used as appropriate. Avoid introducing too many irritating products together.
Focus: clear pores & prevent new lesionsCombination topical treatments are common. Some patients require a limited course of oral medication. Antibiotics should not be the only acne treatment.
Focus: fewer new breakoutsDeep or repeatedly scarring acne needs prompt specialist review. Isotretinoin may be appropriate for selected patients with counselling, contraindication checks and monitoring.
Focus: high scar-risk acneGood acne care is not a fixed package of facials, peels or devices. The aim is to stop new lesions first. Additional procedures may be considered according to clinical need, suitability and availability.
The following are treatment categories, not a prescription. A dermatologist selects and combines them according to lesion type, severity, past response, age, pregnancy potential and safety considerations.
Adapalene, tretinoin or other selected retinoids help prevent comedones. They may initially cause dryness and must be avoided during pregnancy or when planning pregnancy.
Benzoyl peroxide helps treat inflammatory acne. When used with topical or oral antibiotics, it also helps reduce antibiotic resistance. Antibiotics should not be used alone.
Used selectively for the shortest effective duration alongside appropriate topical therapy, generally including benzoyl peroxide. Antibiotics alone are not a maintenance plan.
Combined hormonal contraception or spironolactone may be considered after checking indications, contraindications and reproductive plans.
An important option for appropriately selected patients, requiring counselling, pregnancy prevention where relevant, and monitoring.
Gentle cleansing, non-comedogenic moisturiser and sun protection improve tolerability and help manage post-acne pigmentation.
Acne results from an interaction between follicles, oil production, inflammation and Cutibacterium acnes. Genes and hormones influence the pattern. Scrubbing harder cannot solve these underlying processes.
These factors can aggravate acne in some people. They are not universal causes, and you do not need to eliminate everything.
Never stop prescribed medicines without medical advice. Dietary links vary by individual; no restrictive diet is routinely required.
Chest, shoulder and upper-back acne may need a different practical routine. Deep, tender body acne or lesions leaving marks or scars deserve assessment.
A straightforward assessment followed by a practical treatment plan. Routine hormone testing is not necessary for every acne patient; investigations are considered when indicated.
Assess types of lesions, affected areas, current marks/scars and how much acne is affecting you.
Discuss products, medicines and, when relevant, menstrual patterns or other hormonal symptoms.
Choose a suitable routine, explain expected irritation and set a follow-up to judge response.
If possible, note which creams or tablets you have already tried, bring product or prescription names, and mention any medicine allergies. Tell your dermatologist if you are pregnant, breastfeeding or planning pregnancy, because some acne medicines are unsuitable.
Mild, temporary irritation can occur with some topical acne treatments, but severe reactions should not be ignored.
Topical retinoids and benzoyl peroxide can cause tightness, flaking or mild stinging. A gentle moisturiser and adjusted frequency may help when advised.
Response is gradual; improvement often takes 6–8 weeks or longer. Persistent worsening should be reassessed rather than dismissed as inevitable “purging”.
Marked swelling, blistering, intense burning or suspected allergy need review. Seek urgent care for breathing difficulty or facial/tongue swelling.
Keep your routine consistent and gentle. Expensive products and frequent facials are not automatically better.
Brief answers to questions frequently raised during acne consultations.
Many topical regimens need about 6–8 weeks before fewer new pimples are apparent. More complete improvement can take longer, and maintenance may be needed. Overnight cures are not realistic.
Yes. Deeper inflammatory acne has a higher scarring risk, but even smaller inflamed lesions can sometimes scar. Early appropriate treatment lowers the likelihood of scarring, although it cannot guarantee prevention.
No. Brown or red marks generally involve colour changes, whereas true scars involve altered skin texture such as pits or thickened areas. The treatments differ.
Not routinely. They are considered when there are suggestive symptoms or signs, such as irregular periods, excessive facial hair or other features of androgen excess.
No. Acne involves multiple biological factors and is not caused by poor cleanliness alone. Some dietary patterns may affect acne in some people, but there is no universal food ban that treats everyone.
No. It is an important option for selected severe, scarring or treatment-resistant cases, but not for every patient. Assessment, side-effect counselling and appropriate monitoring are essential, along with strict pregnancy-prevention precautions for anyone who could become pregnant.
No. They may be offered as an adjunct in carefully selected cases. Dermatologist-prescribed medicines and a tolerable daily routine are often the foundation of treatment.
Yes. Acne can develop wherever oil glands and follicles are active, including the chest, shoulders and upper back. Deep or painful body acne is a reason to seek assessment.
Yes. Acne can recur, especially when underlying triggers persist. A suitable maintenance routine and periodic reassessment may help reduce future breakouts.
Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU)
Maheshwari Hospital, Dalanwala, Dehradun, Uttarakhand
Consultation ₹800 · Pre-booking required · No advance booking charge