Temples
Hairline begins to recede in an M-shaped pattern.
Male pattern hair loss usually develops gradually: hair at the temples, front or crown becomes thinner and shorter before some areas become visibly bald. A diagnosis-led treatment plan aims to preserve existing follicles and, in some people, improve hair density.
Consultation ₹800 · Pre-booking required · No advance booking payment
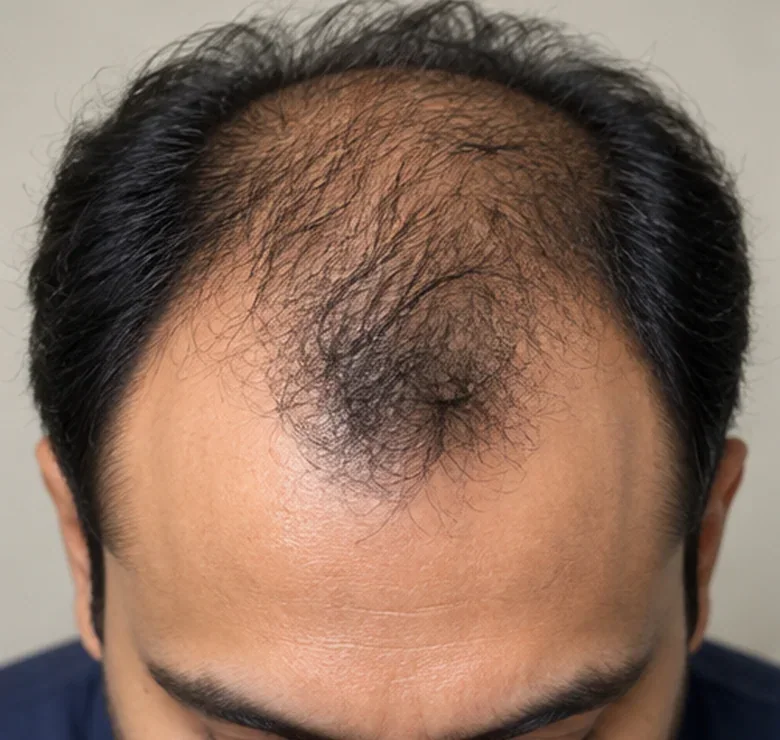
These clues help distinguish one kind of hair loss from another—but images and symptoms alone cannot confirm a diagnosis.
Hairline begins to recede in an M-shaped pattern.
A widening thin spot develops at the vertex.
Thick hairs gradually become shorter, finer and lighter.
Untreated thinning often progresses over months to years.
This classification helps patients understand typical progression from an early receding hairline to more advanced crown and top-of-scalp thinning. It is only a guide—an examination is still important because other causes of hair loss can mimic pattern baldness.
Swipe sideways to view all seven stages clearly.
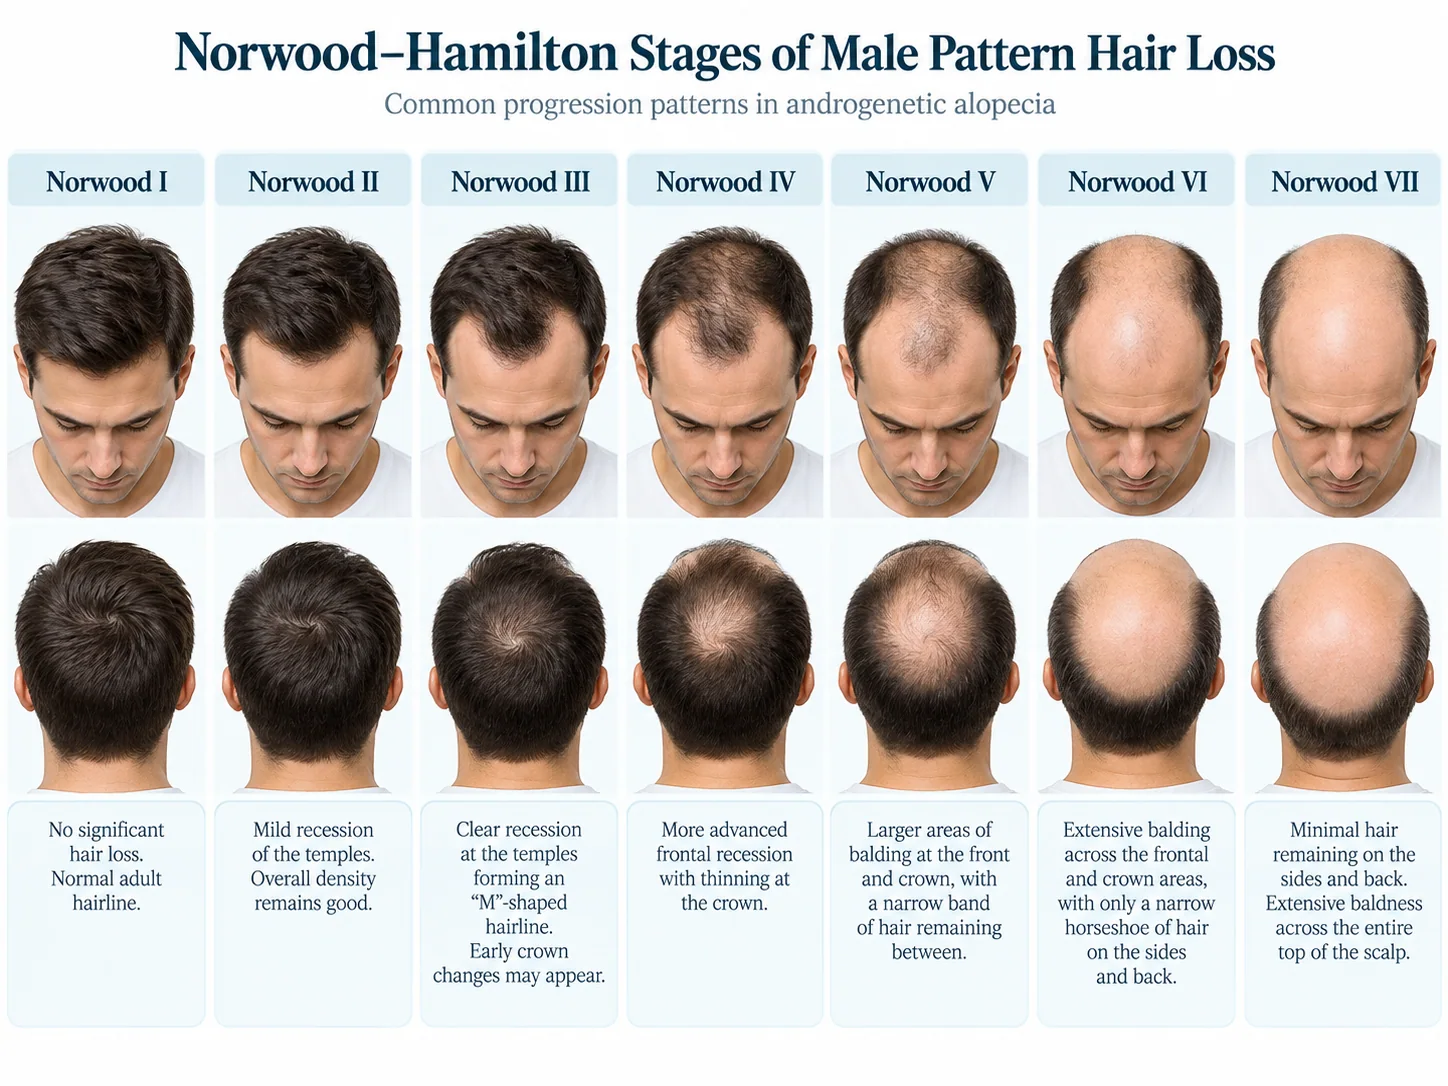
How to use this visual: early stages usually show temple recession or subtle crown thinning, while later stages show wider loss over the top scalp. Treatment aims mainly to slow progression and preserve miniaturising follicles; long-standing completely bald areas usually respond less to medicine. This AI-generated teaching illustration is a guide, not a diagnostic photograph.
Male androgenetic alopecia is a common inherited condition. Genetically susceptible follicles gradually miniaturise under androgen signalling, especially dihydrotestosterone (DHT). It is not simply a consequence of washing hair frequently, wearing a cap or having high testosterone.
Miniaturisation explains why a man may notice thin, short hairs before an area appears bald. The earlier effective treatment starts, the more functioning follicles may be available to preserve. Advanced areas with long-standing loss are less likely to respond to medication.
Clinical history and scalp examination guide whether trichoscopy, laboratory tests, microscopy or biopsy is needed. Not every patient requires all investigations.
Age at onset, family history, temple and crown distribution, speed of change and prior treatments.
Clinical examination and trichoscopy to look for variation in hair-shaft diameter, miniaturisation and other scalp disease.
Typical isolated male pattern hair loss often needs no broad blood-test panel. Tests are directed by unusually diffuse, sudden or symptomatic shedding.
Management depends on the actual condition, its severity, age, medical history and your goals. Counselling about realistic expectations, duration of treatment and possible side effects is an important part of care. Procedures are not a replacement for treating the underlying cause.
Topical minoxidil is an established treatment for suitable patients. Apply it to the scalp as directed and use it consistently; improvement is gradual, and an assessment often requires 6–12 months. Temporary increased shedding can occur during the first weeks. Scalp itching, dryness or irritation may occur, while unwanted facial hair can result from transfer beyond the scalp. It may improve the thickness of miniaturising hairs, but complete regrowth in long-standing bald areas is unlikely. Benefits usually diminish after treatment is stopped.
Oral finasteride reduces DHT activity and can slow further thinning in appropriately selected adult men; benefits generally take several months and require ongoing treatment. Possible adverse effects include reduced libido, erection or ejaculation difficulties, and mood changes. Sexual symptoms have sometimes been reported to persist after stopping. If depressed mood or suicidal thoughts develop while taking finasteride 1 mg for hair loss, stop taking it and contact your doctor promptly. Medical history, individual concerns and fertility plans should be discussed before prescribing. Other medication options require an individual risk–benefit discussion and some uses may be off-label.
Platelet-rich plasma (PRP) or growth-factor concentrate (GFC) procedures can be considered as adjuncts for selected patients, not substitutes for established medical treatment. Improvement is variable and not guaranteed. Several initial sessions and periodic maintenance may be discussed, depending on response; protocols and supporting evidence differ, particularly for GFC. Temporary pain, pinpoint bleeding, swelling or scalp tenderness can follow injections, and infection is uncommon when appropriate sterile technique is used. Costs, expectations and the need for continued medical therapy should be discussed before treatment.
Hair transplantation may be considered for carefully selected patients with adequate donor hair and stable expectations, usually after discussing medical stabilisation. Transplantation is not presented as an in-clinic service here.
Hair grows slowly. These are broad milestones, not a guaranteed timetable for improvement.
Confirm the pattern and establish realistic goals.
Some patients notice temporary shedding or little visible change; consistency matters.
Assess stabilisation and photographic density change; many treatments require continued use.
Clear answers without unrealistic promises or one-size-fits-all treatments.
Do not begin or discontinue prescription treatments solely from a webpage. A dermatologist can identify overlapping disorders and discuss benefits, contraindications and follow-up. All clinical images on this page are AI-generated illustrations—not photographs of patients or treatment results.
Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU)
Maheshwari Hospital, Dalanwala, Dehradun · Consultation ₹800