01
Plaque psoriasis
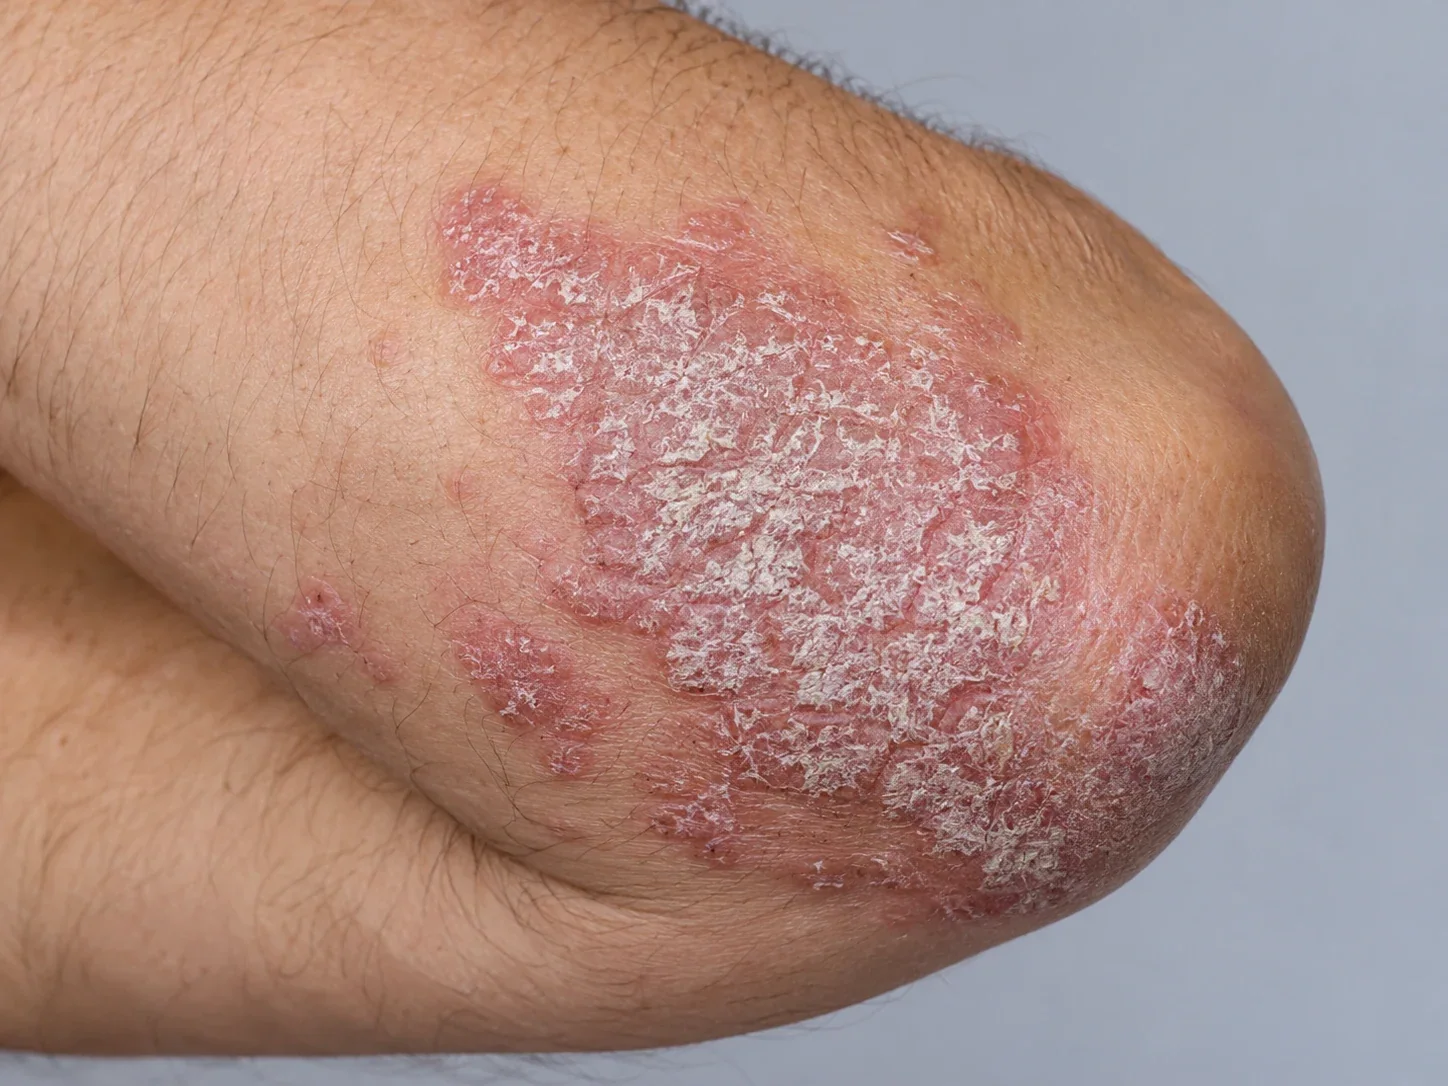
Well-defined, thick, scaly plaques, often on elbows, knees or trunk.
Long-term control. Healthier skin. Better quality of life.
Psoriasis can affect the skin, scalp, nails and sometimes joints. Find an evidence-based treatment plan for your type, severity, symptoms and long-term needs.
Consultation ₹800 · Maheshwari Hospital, Dalanwala, Dehradun
 Psoriasis care · Skin, scalp & nails
AI-generated medical illustration for education, not a patient photograph.
Psoriasis is a chronic, immune-mediated inflammatory condition. It causes scaly skin patches and can also involve nails or joints. It is not contagious. Many patients achieve good control, although the condition may relapse.
MBBS (IMS-BHU), MD (IMS-BHU)
Dermatologist & Venereologist · Dehradun
Dr Neeraj Garg completed both MBBS and MD at the Institute of Medical Sciences, Banaras Hindu University (IMS-BHU). He provides evidence-based assessment for skin, hair, nail and sexually transmitted conditions, with individualised care, clear counselling and patient privacy.
 MBBS + MDBoth from IMS-BHU
Appearance and affected areas vary. These AI-generated examples illustrate common patterns, but no image can confirm the diagnosis on its own.
Well-defined, thick, scaly plaques, often on elbows, knees or trunk.
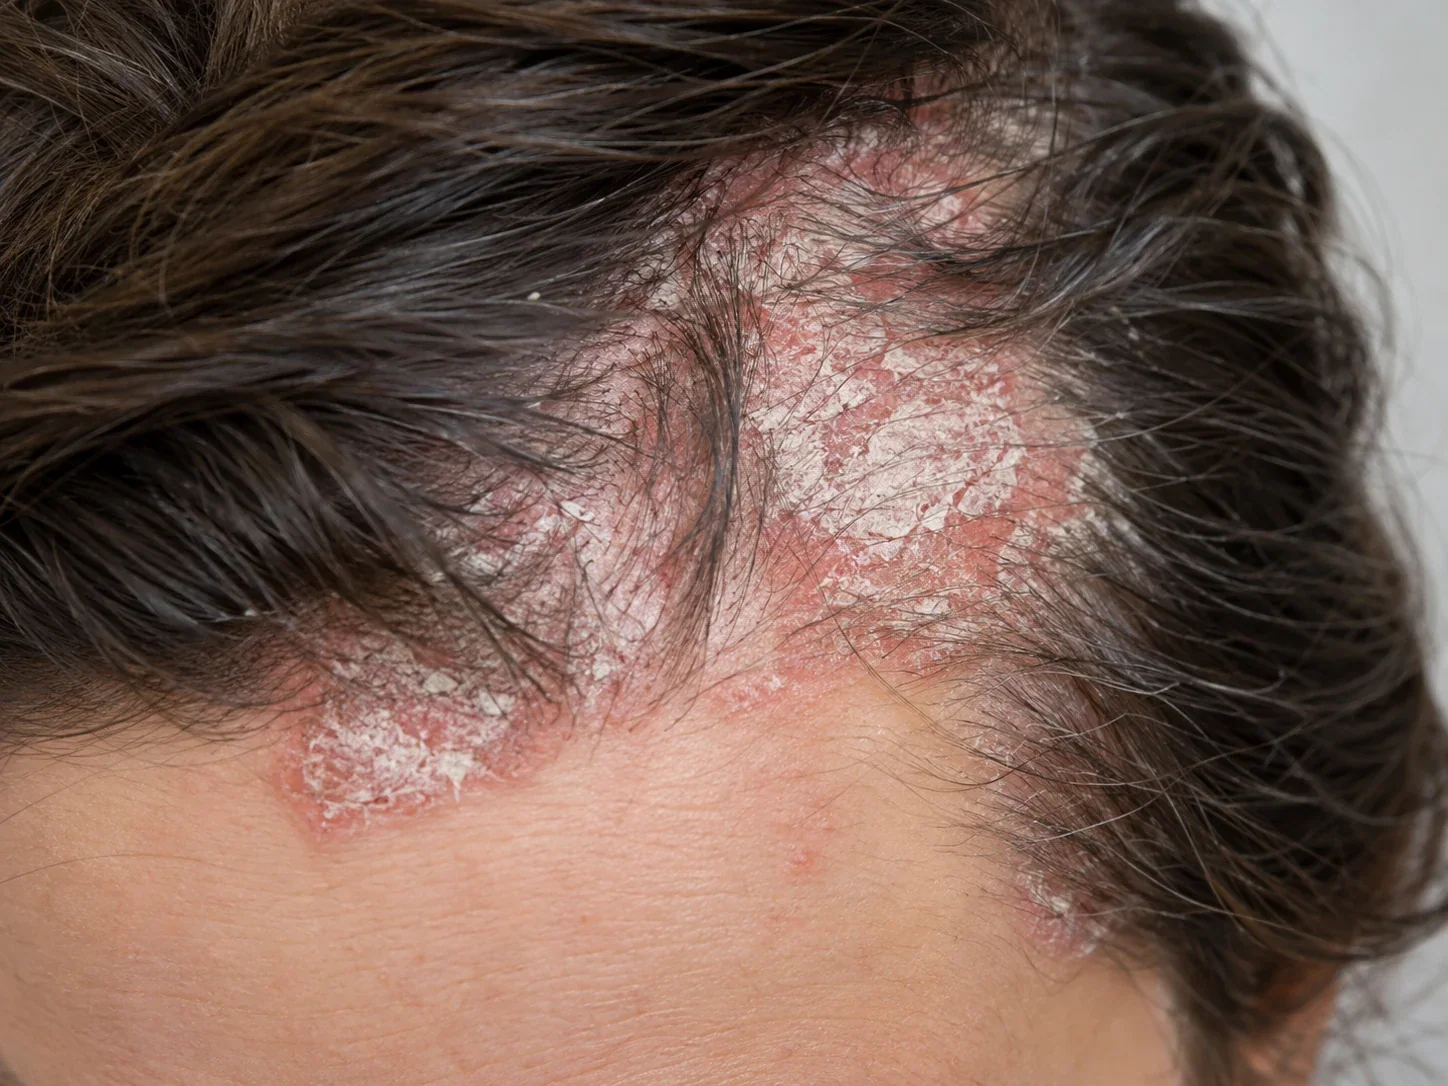
Scaly, inflamed patches on the scalp, sometimes extending beyond the hairline.
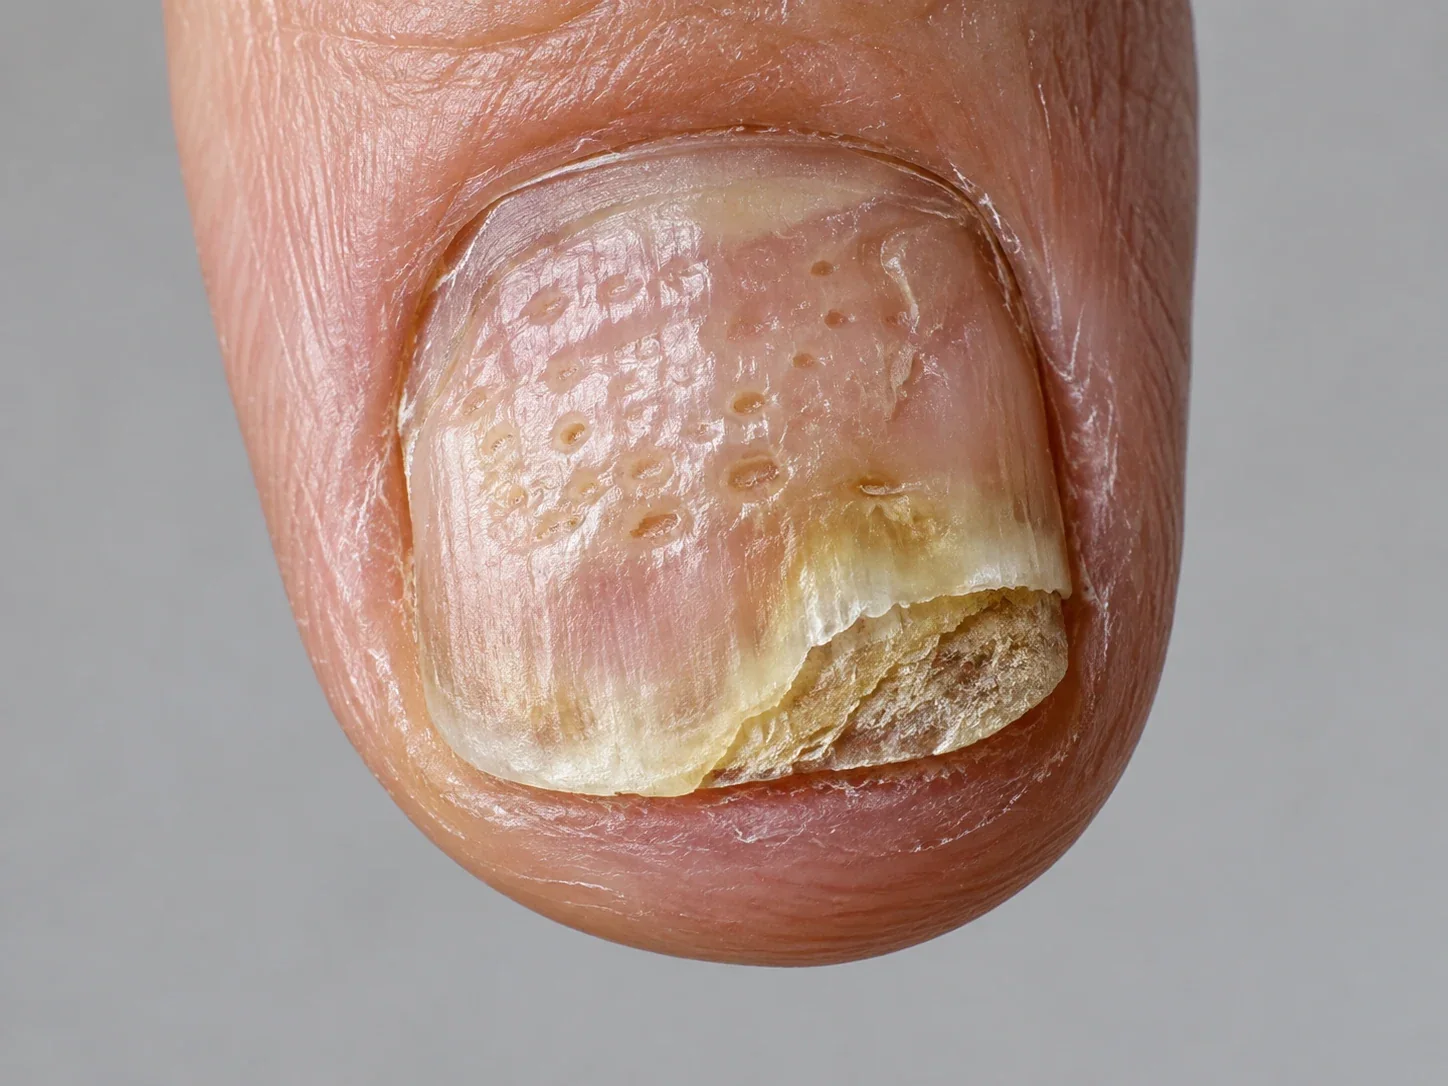
Pitting, nail separation or thickening; nail fungus may look similar.
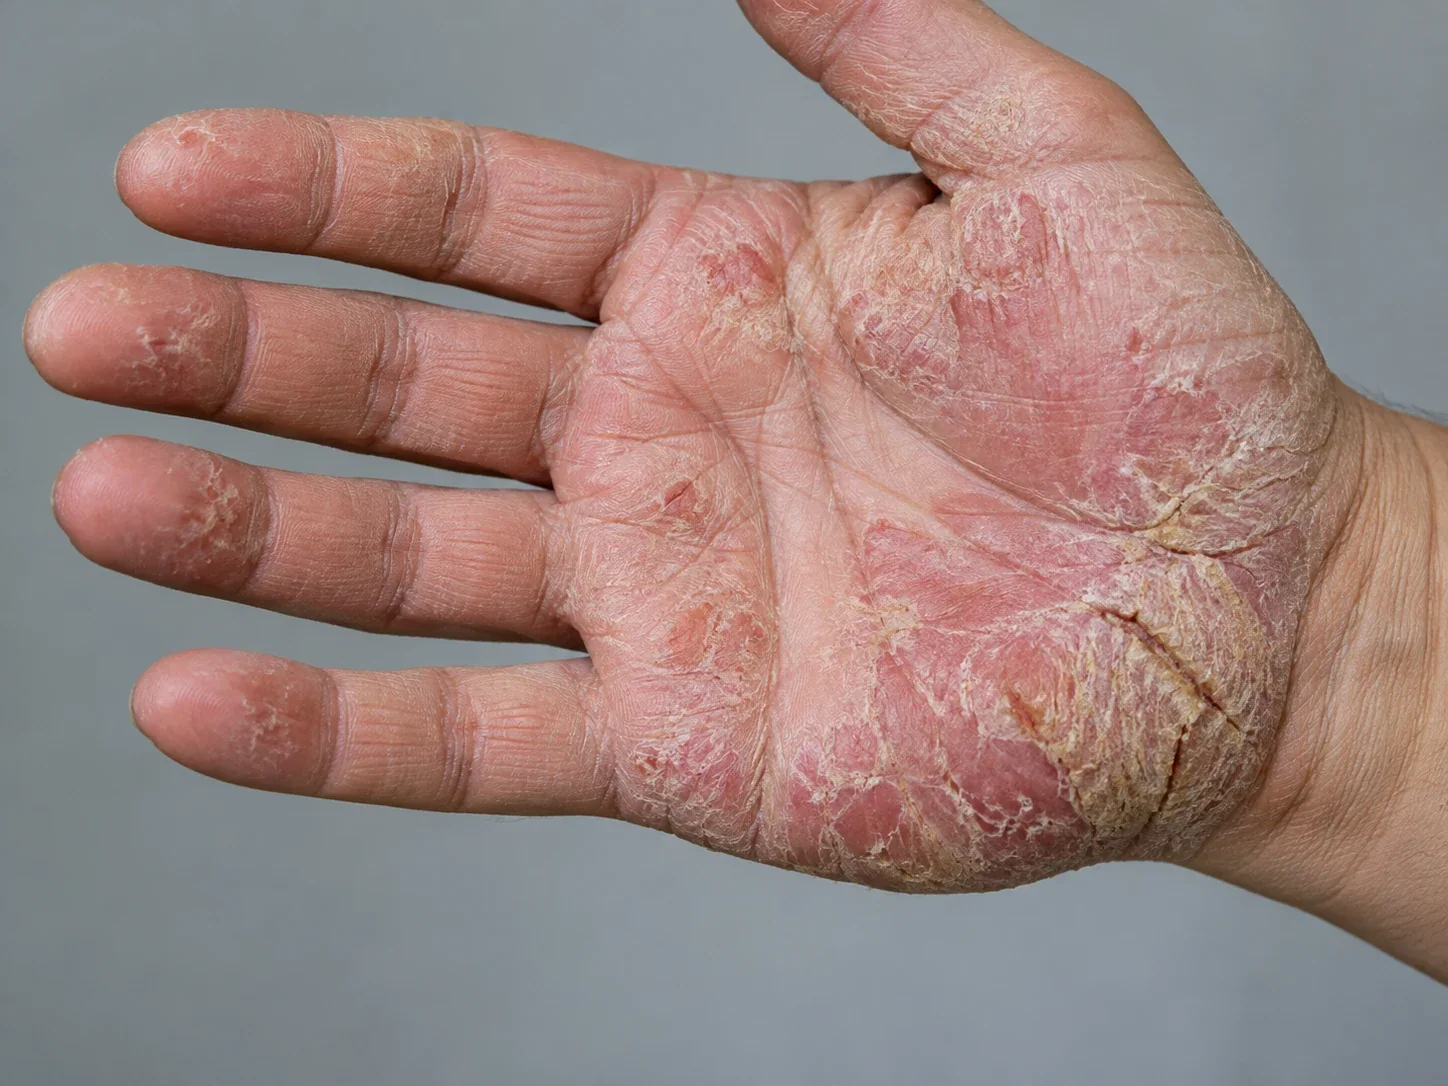
Thick plaques and cracks on palms or soles can affect daily tasks.
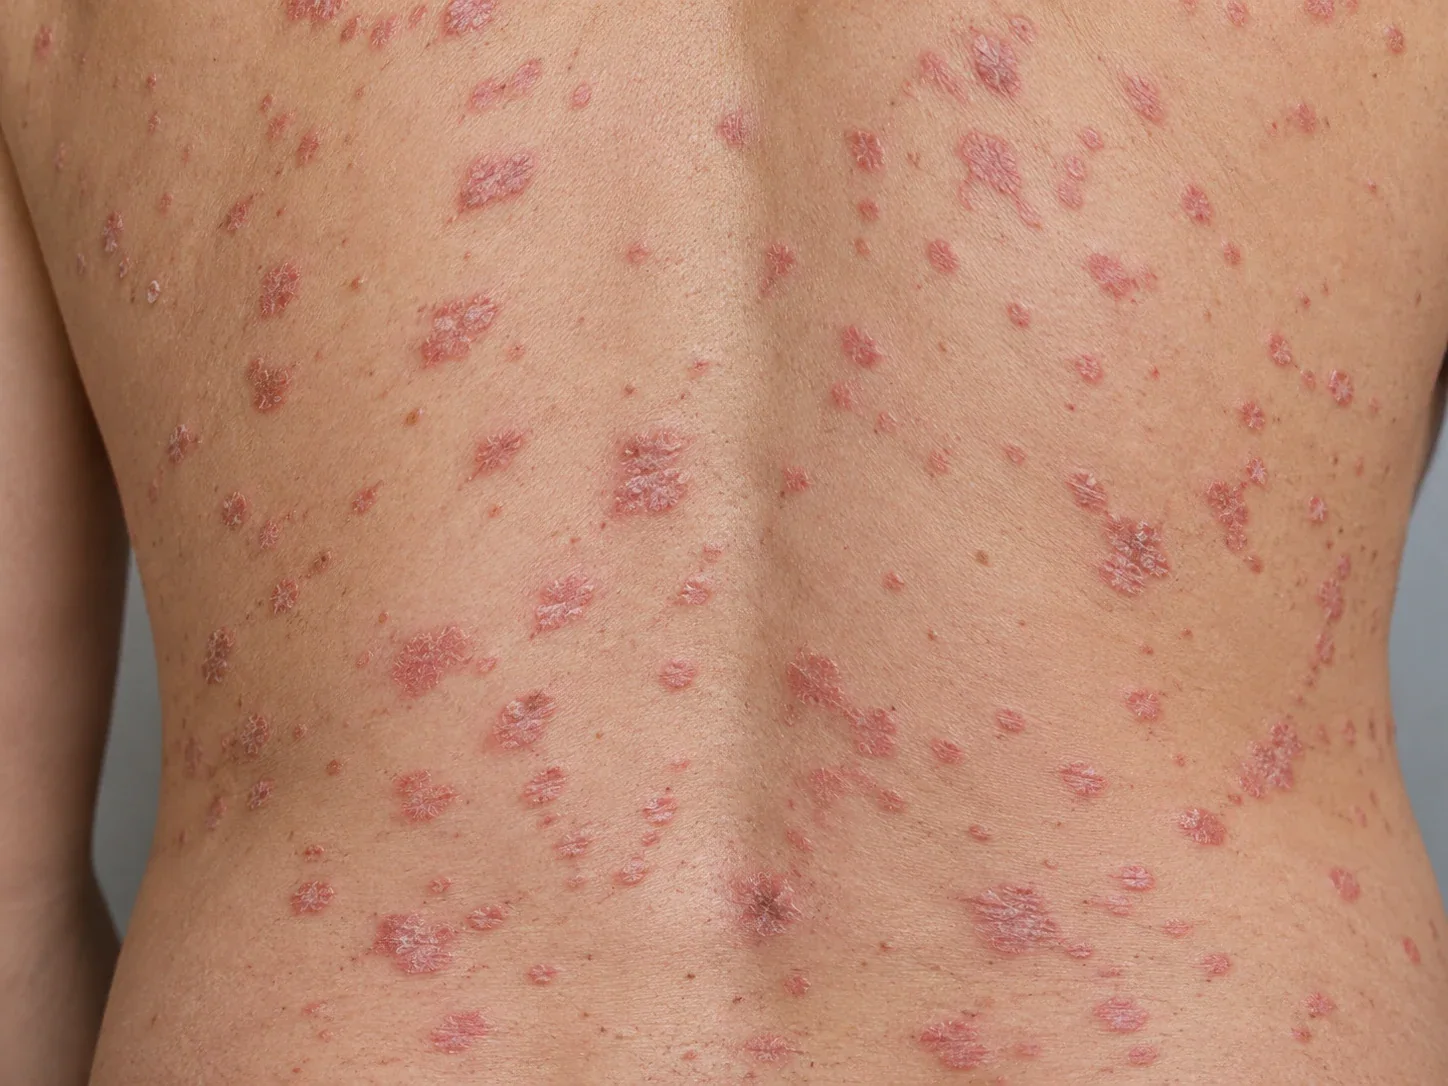
Numerous small, drop-like spots; some episodes follow a throat infection.
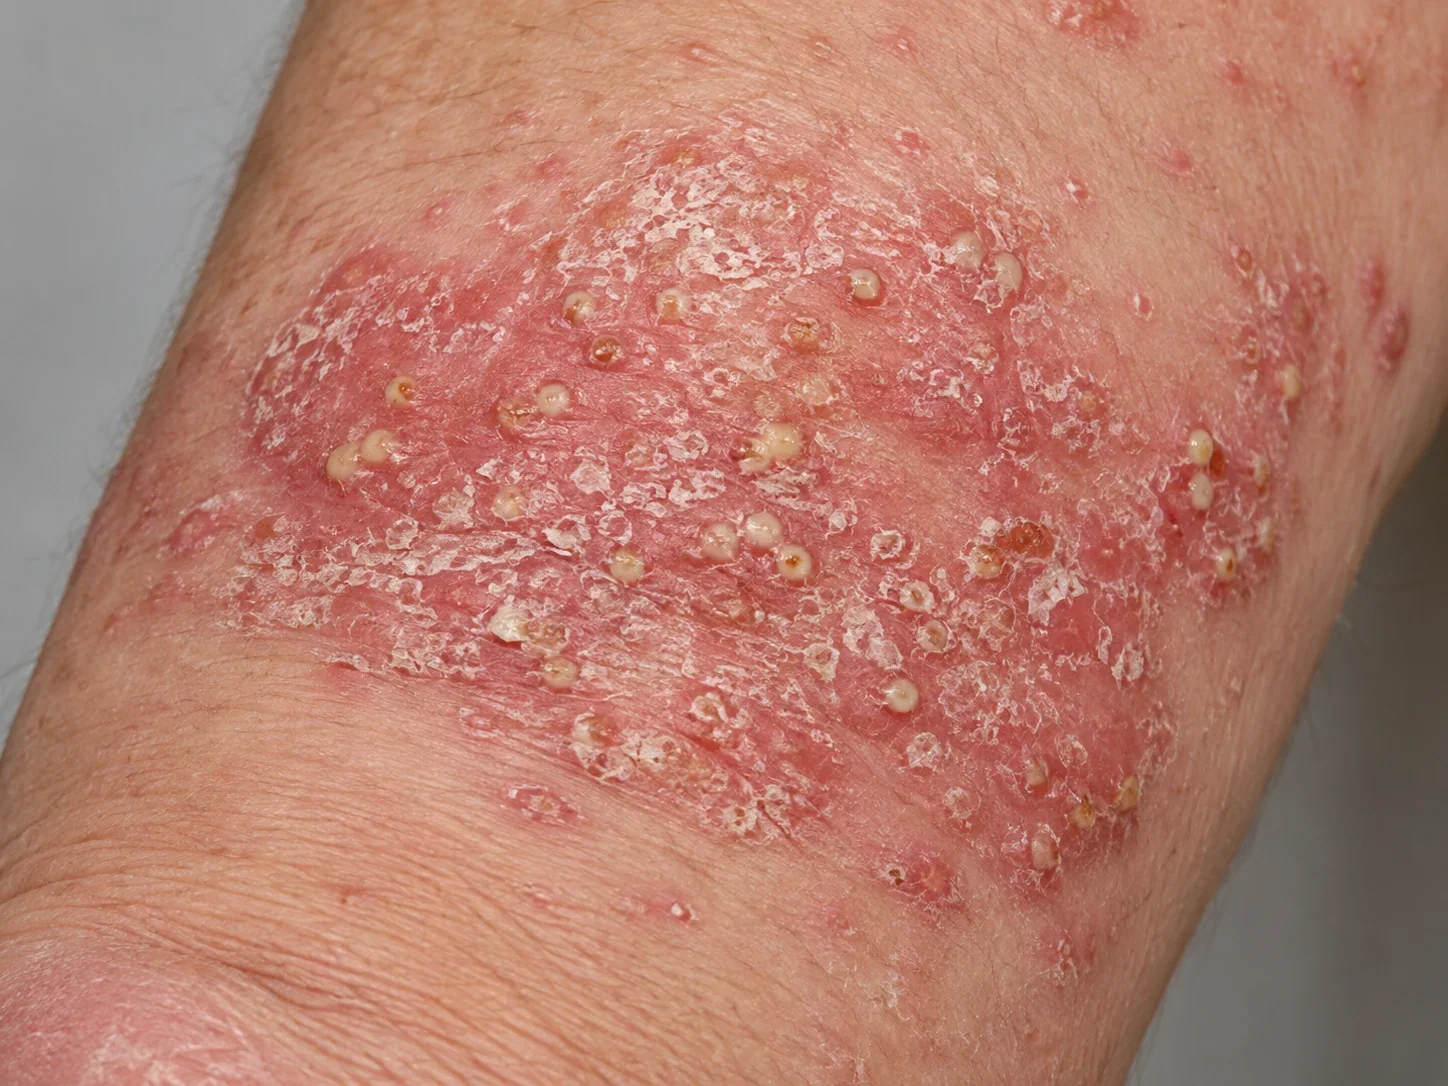
Sterile pustules and inflamed skin; widespread disease can be urgent.
All clinical images on this page are AI-generated educational examples. Actual appearance varies with skin tone, disease activity and individual presentation.
The extent of visible scale is not the only measure of disease impact. The scalp, nails, palms, soles, skin folds and joints may need particular attention.
Swollen or painful joints, persistent stiffness, inflammatory back pain or sausage-like swelling of a finger or toe may suggest psoriatic arthritis. Early evaluation matters.
Recurrent disease, nail damage, scalp plaques or painful palm and sole involvement can interfere with work, sleep and confidence—even if the affected area is small.
Extensive redness, widespread pustules, fever, marked pain or feeling unwell call for urgent medical assessment rather than trying another over-the-counter cream.
The aim is to confirm the pattern, recognise any joint involvement, assess severity and choose a manageable treatment plan.
Review duration, distribution, previous treatment, triggers, scalp, nails, palms, soles and other sensitive areas.
Ask about pain, swelling or stiffness; review medicines and relevant associated health conditions.
Choose appropriate topical treatment, phototherapy or systemic options based on severity and safety.
Assess improvement, side effects and relapse prevention. Some treatments require blood tests and ongoing monitoring.
Psoriasis is usually diagnosed by history and skin examination. A dermatologist also considers severity, the effect on daily life and the possibility of psoriatic arthritis.
Examine the pattern. Review plaques, scalp, nail changes, skin folds, palms, soles and involvement at sensitive sites. Other conditions such as eczema or fungal disease may resemble psoriasis.
Assess severity and impact. Extent matters, but sleep, pain, cracks, visible sites, quality of life and previous treatment response can be equally important.
Choose tests selectively. A skin biopsy is not usually needed. Lab investigations may be needed before systemic therapy, and suspected psoriatic arthritis merits appropriate rheumatology assessment.
Thickened, discoloured or lifting nails can have several causes. Fungal microscopy or culture may be appropriate when the diagnosis is uncertain.
Joint symptoms can occur even with limited skin disease. Mention morning stiffness, heel pain, swollen digits or persistent back pain during consultation.
Alongside visible plaques, it is important to consider overall health and how psoriasis affects everyday life.
People with psoriasis have higher rates of psoriatic arthritis, excess weight, high blood pressure, diabetes and cardiovascular disease. This does not mean everyone with psoriasis will develop these problems.
Assessment may include questions about joint symptoms and relevant health risks. Blood pressure, weight, blood sugar or other checks can be considered according to individual needs, with appropriate medical follow-up.
Itching, visible plaques, discomfort and repeated flares may affect sleep, confidence, relationships, work or mood. The impact can be significant even when only a small area of skin is involved.
Tell your dermatologist if psoriasis is affecting your daily life or emotional wellbeing. This helps guide treatment choices, and further support can be considered when needed.
Medication selection depends on type, location, severity, other health conditions, past response and patient preference. The options below are examples, not a prescription for every patient.
Prescription corticosteroids, vitamin-D analogues and selected combinations help many patients with localised plaques. Scalp, face and skin-fold disease require site-appropriate formulations and caution.
NB-UVB can be considered for selected patients with more widespread or persistent psoriasis. Treatment requires a planned schedule and appropriate medical supervision.
Moderate-to-severe or highly burdensome psoriasis may warrant systemic therapy. Examples include methotrexate, ciclosporin, acitretin, apremilast or suitable biologics, with screening and monitoring as appropriate.
There is currently no guaranteed permanent cure. However, appropriate treatment can greatly reduce plaques, improve comfort and quality of life and keep the disease controlled for long periods. Some patients need ongoing maintenance care.
Psoriasis is often a relapsing condition. Triggers vary between individuals, and a recurrence does not automatically mean treatment failure.
Stress can worsen symptoms in some people. Managing sleep and stress supports treatment but does not replace medicines.
Certain infections, particularly streptococcal infection, may precede guttate psoriasis in susceptible individuals.
Scrapes, friction and skin injury can trigger new plaques in some patients, a reaction known as the Koebner phenomenon.
Winter dryness may worsen scaling. Use gentle cleansing and regular moisturiser rather than harsh exfoliation.
Smoking and heavy drinking are linked to poorer psoriasis outcomes. Reducing these exposures supports overall health.
Some medicines may aggravate psoriasis in susceptible people. Discuss possible triggers and medication changes with the prescriber.
These steps can reduce discomfort and help maintain skin health, but they do not replace appropriate treatment of active disease.
Use an appropriate moisturiser, especially after bathing, to reduce dryness and scaling.
Do not scrape plaques or pick at the scalp and nails; injury and irritation may worsen psoriasis.
Use scalp products gently and keep nails short. Mention persistent nail pain, lifting or changes in colour.
Long-term or repeated unsupervised use can cause adverse effects and delay appropriate treatment.
Report stiffness, swollen fingers or toes and persistent joint pain without waiting for the skin to worsen.
Manage weight, smoking, alcohol and other cardiovascular risk factors with appropriate medical advice.
No. Psoriasis does not spread through touching, towels, food or close contact. It is an immune-mediated inflammatory disease, not an infection.
There is no guaranteed permanent cure, but modern treatment can control symptoms for long periods. The plan may need adjustment when psoriasis flares.
Yes. Psoriatic arthritis can cause swollen or painful joints, morning stiffness, heel pain or swollen fingers and toes. Tell your dermatologist early; suspected arthritis needs appropriate assessment.
No. Many patients improve with topical therapy. Phototherapy or systemic medicines are considered for selected cases based on severity, difficult sites, quality of life and treatment response.
Scalp psoriasis can cause heavy scale and itching. Temporary hair shedding may occur, particularly with scratching or severe inflammation, but many people regain hair as the scalp improves.
Some scaly rashes look alike. Examination and occasionally KOH testing help distinguish them. Steroid creams may worsen some fungal infections if the diagnosis is wrong.
No. Nail pitting, separation or thickening can reflect psoriasis, fungal disease or other nail disorders. Testing may be useful in uncertain cases.
Not everyone does. Baseline tests and ongoing monitoring depend on the treatment being considered, especially systemic immunomodulating medicines.
Stress, dry weather, skin injury and some infections can trigger flares. There is no single diet that cures psoriasis. Maintaining a healthy lifestyle can support overall health.
Treatment choices change during pregnancy and conception planning. Some medicines, including acitretin and methotrexate, are contraindicated. Discuss plans before starting or stopping medication.
Seek urgent medical evaluation, especially with extensive redness, widespread pustules, fever, dehydration or feeling unwell. Severe forms of psoriasis need immediate specialist assessment.
Not necessarily. Some patients need intermittent topical treatment while others benefit from longer-term maintenance, phototherapy or systemic therapy depending on severity and relapses.
Consult Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU) · Maheshwari Hospital, Dalanwala, Dehradun · Consultation ₹800.